Changes in anticoagulation treatment and associated resolution or persistence of left atrial thrombus. Insights from LATTEE registry
European Heart Journal


Abstract
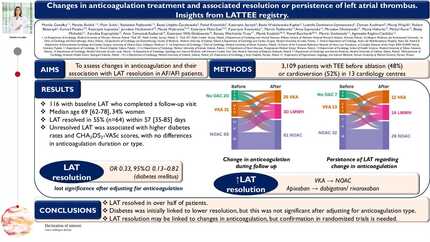
The recent guidelines on atrial fibrillation (AF)/ atrial flutter (AFl) highlight the limited data available on the optimal anticoagulation strategy for patients observed with left atrial thrombus (LAT).
We aimed to determine the changes in anticoagulation treatment and associated resolution or persistance of LAT in patients with AF/AFl.
Consecutive patients with AF/AFl in whom transoesophageal echocardiography (TEE) was performed before direct current cardioversion or ablation in 13 cardiology centres were included.
Of 3109 patients enrolled, 8.0% (n=250) had LAT on TEE, with 46% (n=116/250) undergoing follow-up TEE. LAT resolved in 55% (n=64). Unresolved (vs persisted) LAT was linked to higher diabetes prevalence (45% vs. 25%, p=0.031) and CHA2DS2-VASc scores (4 (3–5) vs. 4 (2–5), p=0.033), while anticoagulation duration and type/dose showed no significant differences.
Patients initially without anticoagulation who started vitamin K antagonists (VKAs) after LAT diagnosis had better LAT resolution (0% risk of LAT) than those prescribed dabigatran (75%), rivaroxaban (50%), apixaban (17%), or low-molecular-weight heparin (LMWH, 40%). Among those on VKAs at baseline, switching to non-VKA oral anticoagulants (NOACs) reduced LAT persistence (15%) compared to continuing VKAs (50%) or switching to LMWH (75%). Dabigatran showed the lowest LAT rates among NOACs (0%). LAT outcomes varied by NOAC transitions. Dabigatran-to-rivaroxaban switches had the lowest LAT risk (25%), followed by rivaroxaban-to-LMWH or remaining on rivaroxaban (40%). Persisting with apixaban was associated with 100% LAT persistence, while switching from apixaban to other NOACs yielded no LAT at follow-up.
Based on our results, following anticoagulation scheme changes may be recommended for LAT resolution: start VKA for anticoagulant-naïve patients, switch VKA to dabigatran, continue dabigatran or rivaroxaban, and change apixaban to another NOAC.
Contributors


You may be interested in