Reduction in heart failure hospitalizations by sacubitril/valsartan; a post-hoc analysis of the PARALLAX trial
European Heart Journal


Abstract
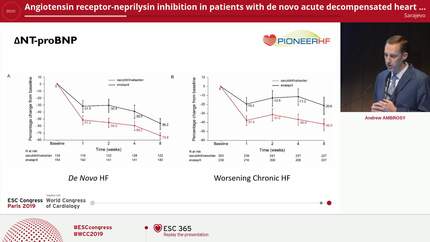
The PARALLAX trial recently showed a significant reduction in plasma N-terminal pro-B-type natriuretic peptide (NT-proBNP) concentrations by angiotensin receptor neprilysin inhibition with sacubitril/valsartan (S/V) compared to standard medical therapy (SMT) in patients with heart failure and ejection fraction ≥40%. As NT-proBNP reductions have been associated with a reduction in future heart failure hospitalizations (HHF), we aimed to investigate the impact of S/V on this endpoint in comparison to standard medical therapy.
The PARALLAX study was a 24-week, randomized, active-controlled, parallel group study to evaluate S/V compared to SMT for comorbidities. Eligible patients were stratified into three strata according to their individual RASi treatment (ACEi, ARB, ACEi/ARB-naïve) and randomized within each stratum 1:1 to S/V (N=1281; target dose (td), 97/103 mg b.i.d.) or individual comparator (N=1285; enalapril (td 10 mg b.i.d), valsartan (160 mg b.i.d.), or placebo). Hospitalizations for cardiac failure reported as serious adverse events by investigators were analysed in this post-oc secondary analysis.
2566 patients with heart failure and LVEF ≥40%, were randomized to receive either S/V or SMT according to RASi stratum (n=1,016 ACE inhibitor stratum, n=1,174 ARB stratum, n=326 no RAS stratum). After 12 weeks, adjusted geometric mean ratio of NT-proBNP showed a 16.4% greater reduction sith S/V vs. SMT (p<0.0001). S/V reduced the risk for cardiac failure events leading to hospitalization by 51% (hazard ratio (HR) 0.49; 95% CI 0.30, 0.81; p=0.005). Similar results were obtained in all three strata: HR 0.55 (0.25–1.19) in ACE inhibitor stratum, HR 0.50 (024–1.02) in ARB stratum and HR 0.37 (0.10–1.38) in no RAS stratum.
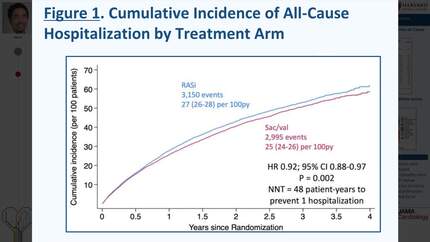
The significant reduction of NT-proBNP plasma levels by S/V in comparison to SMT in PARALLAX was associated with a significant reduction in heart failure hospitalisations. These results, together with evidence from the PARAGON trial, support the use of S/V in HFpEF for avoiding heart failure hospitalizations.
Type of funding sources: Private company. Main funding source(s): Novartis

You may be interested in