Comparative efficacy and safety of de-escalation, abbreviation, and standard potent P2Y12 inhibitor–based dual antiplatelet therapy strategies after acute coronary syndrome: a network meta-analysis
EHJ - Open


Abstract
Potent P2Y12 inhibitor-based dual antiplatelet therapy (DAPT) is the default antiplatelet strategy after acute coronary syndrome (ACS), though de-escalation to clopidogrel-based DAPT and abbreviated DAPT followed by potent P2Y12 inhibitor monotherapy are increasingly adopted to mitigate bleeding risk. However, their relative efficacy and safety remain uncertain.
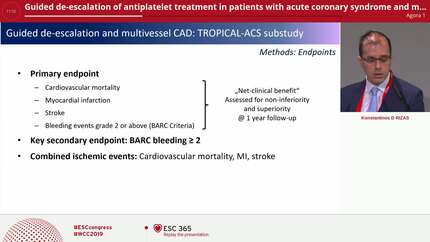
Network meta-analyses of randomized controlled trials were performed to compare three guideline-endorsed strategies: (i) short-term potent P2Y12 inhibitor-based DAPT de-escalation to clopidogrel-based DAPT, (ii) abbreviated DAPT followed by potent P2Y12 inhibitor monotherapy, and (iii) standard 12-month potent P2Y12 inhibitor-based DAPT. The primary efficacy endpoint was major adverse cardiovascular events (MACE). Secondary efficacy endpoints included all-cause mortality, cardiovascular mortality, myocardial infarction, stent thrombosis, and stroke. The primary safety endpoint was major bleeding. The key net clinical endpoint was net adverse clinical events (NACE). PROSPERO (CRD420251144892) Seven randomized controlled trials involving 20 673 patients were included. Both the de-escalation and abbreviation strategies significantly reduced major bleeding (RR 0.43, 95% CI 0.25–0.74,
Following ACS, both de-escalation to clopidogrel-based DAPT and abbreviated DAPT followed by potent P2Y12 inhibitor monotherapy effectively reduce bleeding risk without compromising ischaemic protection. Given that the only available comparison between the two simplified strategies was indirect and showed comparable MACE and NACE outcomes, further research is warranted to determine the optimal individualized approach.
Contributors

You may be interested in