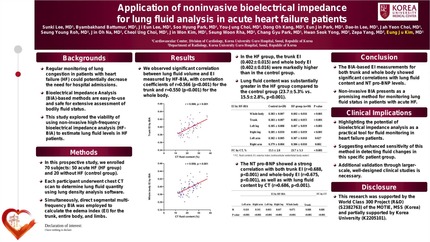
AbstractPulmonary congestion is a major determinant of symptoms, hospitalization, and prognosis in cardiovascular disease, yet its quantitative assessment remains challenging. Remote dielectric sensing is a non-invasive electromagnetic method that provides a quantitative estimate of pulmonary fluid content within ∼1 min. This narrative review summarizes the principles, validation, clinical interpretation, applications, and limitations of remote dielectric sensing. In a validation study of 46 hospitalized patients, including 28 with heart failure, remote dielectric sensing correlated with computed tomography-derived high-attenuation lung area (r = 0.65, P < .001). In a prospective study of 153 patients with heart failure, remote dielectric sensing correlated with lung ultrasound B-line count (r = 0.544); a threshold of 34.5% identified lung ultrasound-defined pulmonary congestion with an area under the curve of 0.748, sensitivity of 73.5%, and specificity of 70.2%. In 133 patients hospitalized with acute heart failure, with a median age of 78 years, 59% men, and a median left ventricular ejection fraction of 57%, an increase in remote dielectric sensing from admission to discharge was associated with all-cause death or heart failure rehospitalisation (adjusted hazard ratio 4.37, 95% confidence interval 1.13–16.81). In a proof-of-concept randomized trial of 100 patients hospitalized with acute decompensated heart failure, the primary endpoint occurred in 2% with remote dielectric sensing-guided care vs 20% with routine care (hazard ratio 0.094). Available evidence supports diagnostic validity and potential prognostic value, but external validation remains limited. Evidence that remote dielectric sensing-guided management improves clinical outcomes remains preliminary. Remote dielectric sensing should be considered a complementary component of multimodality congestion assessment.